Tuesday, October 13, 2020

The testing mess, lack of reliable data on Covid-19, and a hypothesis why

UPDATE:  According to Eric Schneider, MD in the July 25 NEJM, page 300, "The most recent congressional rescue package features $25 billion for testing." So, in the absence of regulation, if you wanted to make a quick killing, all that was needed was to develop a Covid test and offer it in the US between March and October.  Read on.

On January 5 the Chinese scientist who sequenced the first known SARS-2 genome uploaded it to a US database and to the WHO. Within the first 10 days of January a sequence for the Chinese SARS-CoV-2 virus was widely circulated by Edward Holmes of Australia. (He coauthored the March Nature Medicine commentary I criticized here and here.) Holmes works closely with Chinese scientists who passed the sequence to him, possibly without CCP authorization. Here the GISAID international database explains the origin of its reference SARS-CoV-2 strain.
People were able to immediately start devising PCR tests based on the deposited sequences, even without an actual virus. 

After that, as the virus' range extended, scientists around the world started isolating the virus. There have been many thousands of isolations from patients from many countries, and scientists have decoded the genome, i.e., sequenced the virus,  and shown which mutations are occurring when, in different parts of the world. Alina Chan helped create a website that characterizes these strain differences by location, based on sequences uploaded to public databases by scientists around the world.  

The virus has been cultured in many countries, as early as January-February, including by CDC:

1.  Akst J. Australian Lab Cultures New Coronavirus as Infections Climb. The Scientist. https://www.the-scientist.com/news-opinion/australian-lab-cultures-new-coronavirus-as-infections-climb-67031. 

2.  CDC has grown the COVID-19 virus in cell culture, which is necessary for further studies, including for additional genetic characterization. The cell-grown virus was sent to NIH’s BEI ResourcesRepository for use by the broad scientific community.

But the virus cannot be cultured in ordinary hospital labs, because SARS is a designated biological warfare "Select" agent with pandemic potential and must (by US law) be cultured only in high containment laboratories. So culture tests are not now commercially available, but they are being performed under specified conditions.

Testing for the virus is a disaster. There are 186 tests for which FDA has issued emergency use authorizations (PCR, Antibody, and Rapid Antigen tests) that have been in use. I discussed the antibody testing disaster here. Today I focus on the PCR test disaster.

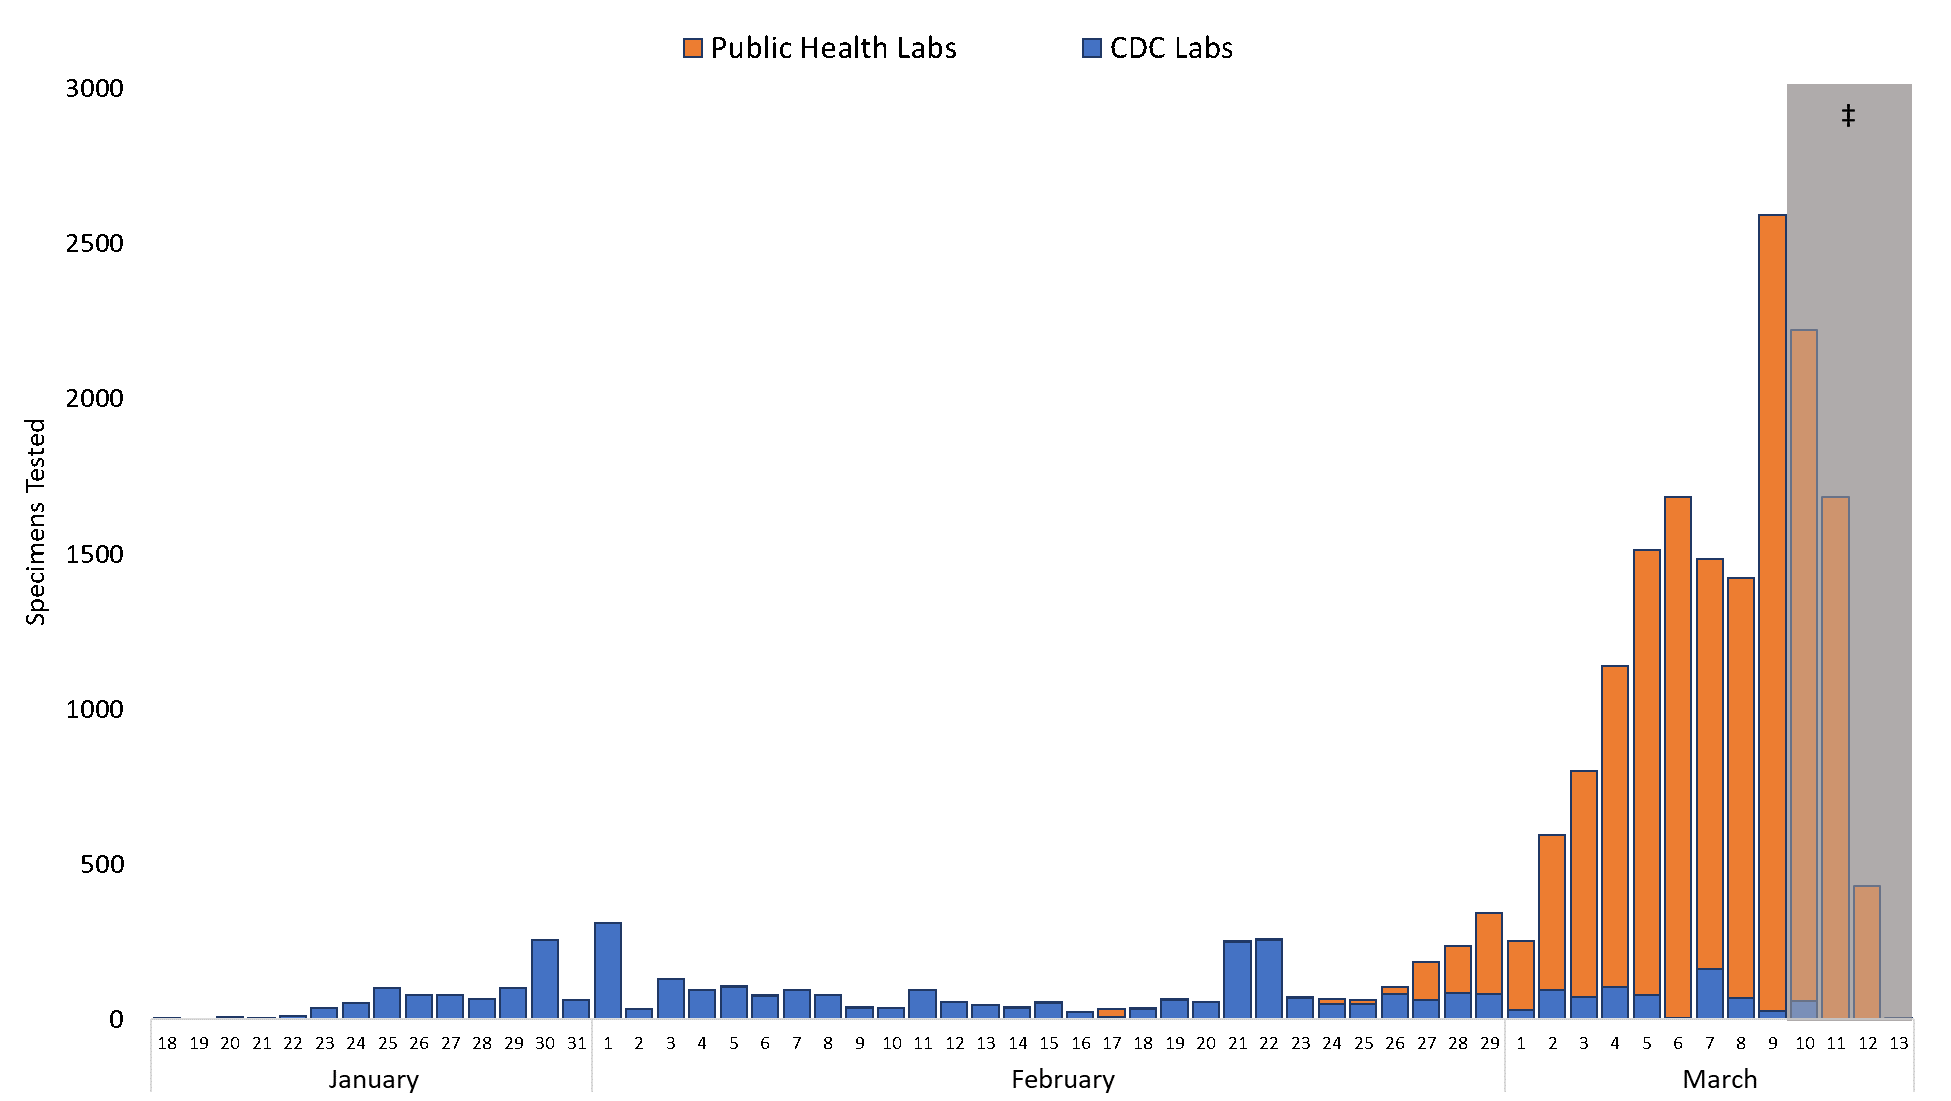
The CDC made the inexplicable decisions to restrict US testing by allowing only the test CDC had developed to be used, throughout January and February. It was a test that was both unnecessarily cumbersome, and faulty. Perhaps because CDC was well aware of the problems, as many labs had pointed them out, CDC would agree to test only those who almost certainly were infected. This harmed lots of patients, and allowed the virus to spread silently for a long time. It further slowed down the development of better and more accessible tests by private, university and state public health labs. CDC's ban on other tests was only lifted on February 28.  (Tom Frieden, former CDC Director, has called for an independent panel to investigate what went wrong.)

(The CDC link below no longer takes you to this CDC graph, which shows how few tests CDC performed during those first two months.) 
Number of specimens tested for SARS CoV-2 by CDC labs (N=3698) and U.S. public health laboratories by date of specimen collection

Possibly germane is the fact that CDC's Covid response was managed by Lisa Messonier, MD, who is Rod Rosenstein's sister. (Rosenstein is the former Deputy Attorney General who, according to the NYT, discussed wearing a wire to record President Trump and suggested that cabinet members consider using the 25th Amendment against Trump.)

By Feb 29, the FDA said it would allow companies to apply for an emergency use authorization (EUA) for their tests, but the procedure was so complicated that only 6 entities applied over the first week. By the middle of March we still didn’t have many tests in the US, so the FDA then said anyone who had developed a test could offer it, without any review, and subsequently send the FDA information on the test performance. This was a
By late March there was an explosion of tests being offered, but nobody had any idea how they compared with each other, nor how sensitive nor specific they were, apart from their manufacturers' claims.

After a while, FDA realized that many of these tests were worthless, and they took a number of tests made in China off the market, but left the others, still over 100 tests. On October 8, FDA announced it would no longer review (and issue) more EUAs for Covid lab tests, in order to "make the best use" of agency resources. 

There are no reliable numbers I know of for how well these tests have performed relative to any gold standard. (There is no gold standard yet.) 

Part of the problem is the virus itself. It doesn’t always stimulate the antibodies that labs are looking for, and some people who get Covid do not make those antibodies in sufficient quantity to be measured. There were similar problems with SARS-1 tests, although, since this virus causes higher nasopharyngeal titers than SARS-1, PCR and antigen tests ought to be more sensitive.  Also, SARS-1 caused 8,000 total cases and SARS-2 750 million, so you would have expected some of those issues to be resolved by now. 

As far as the PCR tests go, it was hoped they would be the gold standard but it has not worked out that way. There are many potential problems with PCR tests. The target nucleotide sequence  that is chosen may not be totally specific to this virus, and cross react with sequences from other microorganisms or ?

A number of different primers (approximately 20 nucleotide long sequences) have been selected for use by different companies. "Laboratories have used different combinations of primers and probes, while some laboratories do not disclose the targets or sequences of their primers/probes..."  We don’t know how they compare with each other. Different machines are being used. Different cycle lengths, i.e., number of doubling cycles, are used in different labs. The different tests have widely varying limits of detection, by 3 plus orders of magnitude. Furthermore, potential lab contamination is always an issue with PCR tests, which can cause false positives. Finally, PCR tests are widely acknowledged to pick up false positives from viral debris, for up to 3 months after patients cease to be infectious. 

If the sample is not obtained carefully, or if it is obtained too early or too late in the course of the illness, the amount of virus on the swab may not reach the limits of detection of the test. 

There is another big wrinkle, when you don't have a near-perfect test, which is termed the "pretest probability." I have not figured out a way to explain it simply. Basically, if a patient has Covid symptoms and SARS-2 is present in the community, a positive test is likely to be accurate.  But if patients don't have SARS-2 symptoms, and/or there is a very low level of SARS-2 circulating, then, of course, truly positive individuals are rare. In this situation, false positive test results may be more common than true positives. The less likely a person is to have a infection, the more likely that a positive test result will be false.

Can the rates of false positives and false negatives be calculated?  Not with the data that are currently publicly available. I doubt CDC and FDA can, either.

The FDA posted a website on October 7 in which FDA says it sent out small test kits to dozens of companies and labs that developed tests, to see how the tests/labs perform. Many labs did not return the results to FDA:


A basic metric for all infectious diseases is the proportion of infected but asymptomatic cases.  Generally these cases develop immunity.  When the WHO has estimated that over 10% of the world's population (>780 million cases) has been infected, surely the great majority have been asymptomatic.  I say this because the WHO says 38 million cases of Covid have been reported, which is under 5% of WHO's estimated number of cases.  Yet we still have no reliable information on the % of asymptomatics, nor of the % of immunes. 

In both the US and the world, cases are rising, but deaths are not.  Death rates in hospitalized patients are a small fraction of what they were. This tells us that the virus is less lethal than it was, and/or treatment has improved, and/or the rise in cases is, at least in part, due to the massive numbers now being tested (about 1 million people per day in the US).  Often, asymptomatic people are being screened, found positive, and designated as cases. My county had an 'outbreak' of Covid in migrant workers who were screened during the blueberry harvest, yet none had symptoms.  We need to know if these positive but asymptomatic people are infectious, but currently we cannot reliably tell.  Perhaps if we knew how many PCR cycles it took for them to produce a positive result, we could estimate the amount of virus present and make an educated guess about infectivity. However, the labs are not required by FDA to provide this information, and they don't.

Coupled with the above confusion is the fact that the media have given us misinformation about most aspects of the pandemic.  Not only is the public confused by this testing mess, and the unwillingness of our public health agencies to commit themselves regarding the validity and meaning of test results, and making sure only quality tests are being used.  We are also befuddled about who gets sick, who gets chronic covid, and why certain treatments have been suppressed while others have been pushed, despite the absence of supportive data.  What exactly are the patterns of age, disease severity and preexisting conditions in Covid patients?  What is the evidence that masking and social distancing have worked in the US?  Why does CDC say to maintain a 6 foot distance while WHO says 3 feet is enough?  A Reuters article noted:

China, Denmark, France, Hong Kong and Singapore recommend social distancing of 1 meter, and many people also choose to, or are required to, wear face masks in public spaces.

Australia, Belgium, Greece, Germany, Italy, Spain and Portugal advise people to keep 1.5m apart. Switzerland this week also reduced the required distance to 1.5m from 2m.

I conclude that we are being played by the government and the media, and every piece of information they present to us I now scrutinize for an ulterior motive, which is often to ramp up the fear of Covid-19.

If you look at the suppression of effective treatments, the falsely elevated case and death numbers, and the prolonged lockdowns which make little sense--because this is a disease that can be effectively treated, even without remdesivir and vaccines, and which, at this point in time, seems to have mortality similar to influenza (2 in 1,000 cases)--you realize we are being subjected to a wholly different agenda than what is claimed.

We are being made to think this pandemic is much more severe than it really is, and the powers that be are doing their best to prolong the emergency. For example, Tony Fauci finds it a challenge to sufficiently scare the public: 
"The wide range of clinical manifestations of the disease ... makes conveying the dangerousness of Covid-19 incredibly challenging," Fauci said in an October 13 interview with STAT.
Our economies are being destroyed and many jobs will never come back. (US 2nd quarter GDP declined 33%, on par with the Great Depression.)

There is a meme that has been used by leaders of multiple countries and the World Economic Forum, and that is “Build back better." 

My best current hypothesis is that the World Economic Forum and its ilk are using the pandemic as a means to destroy the current economy, impoverish many millions of people, and rebuild and finance it to their own specifications.

They are using terms like: preventing climate change, green, save the earth, biodiversity, sustainability, non-racist, equitable, fair-- to sweeten the image of what is to come.

Which seems to be a surveillance state with increased top down control and a reduced standard of living. Green goals may be part of it; after all, the leaders need pristine forests and fields for their own use. Maybe, or maybe not, for our use. 

This view is consistent with statements by Peter Daszak, CEO of EcoHealth Alliance, who is associated with WIV, NIAID, DOD and facilitated transfers of bat coronaviruses found  around the world to scientific and military labs. Quoted in the WaPo, “Pandemics as a whole are increasing in frequency,” said Peter Daszak, a disease ecologist who is president of EcoHealth Alliance, a public health organization [a charitable way to describe his organization--Nass] that studies emerging diseases. “It’s not a random act of God. It’s caused by what we do to the environment."  
Daszac told Slate, "I’ve found that things like land use, change, deforestation, road building, mining, and agricultural intensification are the reasons we push ourselves into wildlife habitat and get infected."
Peter Horby, co-director of the Recovery trial in the UK, which poisoned people with HCQ to prevent its use for Covid, recently tweeted, "this is where we should be headed" regarding a video on bicycle commuting produced by the World Economic Forum. The NYT and other outlets have run similar pieces on how human incursions into nature are destroying nature and producing pandemics.  In August, Tony Fauci and David Morens, in CELL, wrote,
"in a human-dominated world, in which our human activities represent aggressive, damaging, and unbalanced interactions with nature, we will increasingly provoke new disease emergences. We remain at risk for the foreseeable future. COVID-19 is among the most vivid wake-up calls in over a century. It should force us to begin to think in earnest and collectively about living in more thoughtful and creative harmony with nature..."
The pandemic and prolonged lockdowns, which are huge overreactions to the actual seriousness of the illness, coupled with suppression of effective treatments, appear to be the means to get us to the "new normal" aka "Great Reset".

UPDATE October 17:  Not sure there is another agenda here?  Why is the World Economic Forum launching a health passport that could be required to travel?  The Commons Project Foundation and the World Economic Forum announced the launching of international trials for CommonPass, a digital health pass for travelers to securely verify their COVID-19 test status. The project's chief medical officer is Bradley Perkins, a former CDC doctor who was an expert on biological weapons, but could not find any anthrax at the AMI building in Florida, telling staff to continue working there for several days before gross contamination was discovered. “Without the ability to trust COVID-19 tests - and eventually vaccine records - across international borders, many countries will feel compelled to retain full travel bans and mandatory quarantines for as long as the pandemic persists,” said Dr. Bradley Perkins, Chief Medical Officer of The Commons Project. Which was launched a couple of years ago with funding from the Rockefeller Foundation.
Professor Klaus Schwab on The Great Reset

Thursday, October 8, 2020

How many Covid deaths have occurred daily, on average, during the first week of each month in the US?

March              3           (daily average February 29-March 7)

April.         1376           (daily average March 31-April 7)

May            1823          (daily average April 30-May 7)

June              788          (daily average May 3-June 7)

July               525          (daily average June 30-July 7)

August        1056          (daily average July 31-August 7)

September     817         (daily average August 31-September 7)

October         666          (daily average September 30-October 7)

*CURRENT   810       (daily death avg Oct 21-28)

Data obtained from https://covidtracking.com/data/national

What is not being reported:  

  • average age at time of death, 
  • other comorbidities, 
  • % of deaths occurring in nursing homes or assisted living situations, 
  • whether there are excess deaths above the expected number, and 
  • current numbers for all causes of deaths.  

We hear about the outliers, like the first US person proven to get Covid twice, but we don't know about the averages.  We don't know about how the numbers of deaths from suicides, alcoholism and drug abuse compare to previous years. Are we seeing more deaths from cancer, heart attacks or 'sudden deaths'?  These are the data that would allow us to understand the pandemic in perspective.  These are the data that are hidden.

The one person who got Covid twice and died was an 89 y/o woman from Holland being treated for a blood cancer.

Have staff working in congregate living settings been fully trained in infection control?  Been issued adequate equipment?  These important issues are no longer being reported. Why?

How many medical staff are taking prophylactic medications?  We know that half a million Americans (not previously on the drug) purchased HCQ in March and April.  How many Americans are using it now? Is it affecting outpatient morbidity and mortality?  The doctors using it, and willing to come forward, say an unequivocal YES.

Covid data, inadequately reported by CDC, was to be rerouted to HHS.  So far, we have heard no improvement in disease reporting. Will we?

Saturday, October 3, 2020

Useless FDA and CDC admit Covid antibody tests are worthless. Why have they approved them? Why are we paying for them?

I have been meaning to update the information on Covid-19 testing, since it has been such a confusing subject. This post will only cover antibody (aka serology) tests.  And most of the post will be direct quotes from the FDA and CDC websites, because you would probably not believe me if I simply paraphrased the information.  So here is my synthesis, followed by direct quotes from the agencies.

Boiled down, what FDA and CDC say is: 
1.   The presence of antibodies does not mean you have had Covid.  
2.   The test might be positive due to a cross reaction with antibodies from a cold you had.  
3.   Even if you have antibodies and did have Covid, they don't tell us whether or not you are immune.
4.   Even if you are immune today, you may not be immune tomorrow--who knows?
5.   You may have had Covid and have no antibodies
6.   Antibody tests are meaningless for individuals, but might give us useful information at the population level.
7.   Regardless of the result, you still need to wear masks and socially distance.
8.   In a population where less than 5% have had Covid, over 50% of positive results will be false positives.

Yet CDC admits that reinfection is rare.  There are only 3 documented cases of reinfection in the US, so there must be good immunity after infection for most people.  

Bottom line:  why are we doing these tests?  Why hasn't FDA rescinded its emergency approval, since in the majority of the US, most positive results are false positives? And why don't we have better tests? T-cell immunity is probably more accurate, but there are no commercially available T-cell tests for the public. Why are we still measuring antibodies that cross-react with those for the common cold?  Is this another way the federal government is keeping us confused and locked down?

Here are the direct quotes:

FDA:  
"...COVID-19 antibody tests can help identify people who may have been infected with the SARS-CoV-2 virus or have recovered from the COVID-19 infection." 

At this time, researchers do not know whether the presence of antibodies means that you are immune to the coronavirus in the future; or if you are immune, how long it will last."

CDC:  
"...additional data are needed before modifying public health recommendations based on serologic [antibody] test results, including decisions on discontinuing physical distancing and using personal protective equipment. 

...Although serologic tests should not be used at this time to determine if an individual is immune, these tests can help determine the proportion of a population previously infected with SARS-CoV-2

...Recurrence of COVID-19 illness appears to be very uncommon

...However, it remains uncertain to what degree and for how long individuals with antibodies (neutralizing or total) are protected against reinfection with SARS-CoV-2 

...in a population where the prevalence is 5%, a test with 90% sensitivity and 95% specificity will yield a positive predictive value of 49%. In other words, less than half of those testing positive will truly have antibodies. 

...pending additional data, the presence of antibodies cannot be equated with an individual’s immunity from SARS-CoV-2 infection.

...Some tests may exhibit cross-reactivity with other coronaviruses, such as those that cause the common cold. This could result in false-positive test results. Some persons may not develop detectable antibodies after coronavirus infection.

...Serologic testing by itself should not be used to establish the presence or absence of SARS-CoV-2 infection or reinfection."
-------------------------------

And here is a Reuters article quoting the CEO of Roche (which makes Covid tests) claiming that some of the other available tests are worthless.


Friday, October 2, 2020

Fauci's guy prepares us for the bad news that masks and social distancing don't work against mutated virus

The NY POST got some fascinating quotes from the Senior Scientific Advisor in Tony Fauci's office, David Morens.  Morens recently coauthored an article with Fauci (which I discussed here) in which the two of them instructed us that we need to learn to live more harmoniously with nature, or "we will increasingly provoke new disease emergences."  Yup, Fauci and Morens are telling us the pandemic is our own fault.  Here's the full quote:
"The COVID-19 pandemic is yet another reminder, added to the rapidly growing archive of historical reminders, that in a human-dominated world, in which our human activities represent aggressive, damaging, and unbalanced interactions with nature, we will increasingly provoke new disease emergences. We remain at risk for the foreseeable future. COVID-19 is among the most vivid wake-up calls in over a century. It should force us to begin to think in earnest and collectively about living in more thoughtful and creative harmony with nature, even as we plan for nature’s inevitable, and always unexpected, surprises."
Are they hinting that a reduced human population will be less susceptible to pandemics? Or that rural populations need to move?  Is the Great Reset going to control our "interactions with nature"?

Here are excerpts from the NY Post story, in which Morens again seems to be a harbinger of things to come, preparing us for the failures of masks and social distancing to prevent the spread of SARS-CoV-2.  

"David Morens, a virologist at the National Institute of Allergy and Infectious Diseases, said the findings suggest that the virus may become more contagious and that this “may have implications for our ability to control it.”
He said it’s possible that the virus had evolved to resist efforts such as hand-washing and social distancing.
“Wearing masks, washing our hands, all those things are barriers to transmissibility, or contagion, but as the virus becomes more contagious, it statistically is better at getting around those barriers,” Morens told the newspaper."
These phony public health officials have never admitted they were wrong about anything during this scamdemic.  And now, they have started invoking viral mutations (that cunningly defeat masks and distancing) to gin up the fear and keep the scamdemic going, until the public is on its knees.  And the Great Reset can begin.

Trump's former White House physician recommends Hydroxychloroquine, Zinc, Azithromycin, Steroids to treat Covid-19

https://twitter.com/HcqCorona/status/1311988691049553920

Ronnie Jackson, MD, the former White House physician who cared for both Obama and Trump, was just interviewed on Fox News.  He is running for Congress in Texas.  He basically recommended the Zelenko or Raoult protocol for President and Melania Trump, noting that all the drugs were safe.  Above is the video.  Jackson is a retired Rear Admiral and was nominated for VA Secretary, but withdrew, and returned to Texas.

Thursday, October 1, 2020

Emergent BioSolutions will be paid even if the Astra-Zeneca (Oxford) vaccine flops


AstraZeneca was humming right along with its partnered COVID-19 vaccine with the University of Oxford before a sudden trial hold threw its plans into disarray. So what does that uncertainty mean for AstraZeneca's expectant manufacturing partners on the shot? For at least one, it could be no issue at all. 

Despite a major commitment from AstraZeneca to help produce bulk drug substance for the University of Oxford's adenovirus-based COVID-19 shot, Maryland's Emergent BioSolutions isn't likely to feel a financial pinch if the British drugmaker's candidate doesn't make it across the finish line, Cantor analysts wrote in a note to investors Wednesday.

On the heels of AstraZeneca's troubling phase 3 trial hold, Emergent's share price dropped 5% in early Wednesday trading to $100.22 as investors appeared to show concern that AstraZeneca's setback would hit the CDMO's bottom line.

But according to Cantor, Emergent wouldn't likely come out worse for wear if AstraZeneca's candidate flops, as the partners' contract includes protections for Emergent that will see it rake in most of the $174 million owed to it in year one of the deal. 

Part of that deal, signed in July, is an $87 million portion for tech transfer and preparation that is underway, Cantor said. That money has already come Emergent's way, and further contract protections will see Emergent made whole on most of the rest, analysts argued.

The only unknowns in the event of AstraZeneca's failure would be the second and third years of the proposed contract, which could be waived, according to Cantor. However, given Emergent's close relationship with the Department of Health and Human Services' Biomedical Advanced Research and Development Authority (BARDA), another vaccine maker could easily step into AstraZeneca's place to continue driving revenues for Emergent.

Moreover, that alternate partner could secure an even longer-term CDMO contract with Emergent at its Baltimore Bayview facility, largely taking the manufacturer's risk off the table. 


Despite the uncertainty of AstraZeneca's fate in the COVID-19 vaccine hunt, Emergent can rest easy knowing it has at least one other major player in the field on its side. In early July, Johnson & Johnson and Emergent inked a five-year work order worth at least $480 million to help produce the New Jersey-based drugmaker's COVID-19 vaccine candidate.

Emergent will provide "large-scale" drug substance manufacturing for J&J's recombinant DNA shot beginning in 2021, starting with a $480 million order for the first two years of the deal. For the final three years, the partners will use a "flexible capacity deployment model" to provide annual batches as needed, Emergent said.

UPDATE October 14: from FiercePharma:
Emergent has two contracts with J&J. The first, for setup and tech transfer, is worth $135 million in 2020 and 2021. The second, for drug-substance manufacturing, will pay out $480 million in the first two years...
When added to the value of Emergent’s contracts with AstraZeneca and the U.S. Department of Health and Human Services, the company is assured $1.5 billion that “is largely protected from clinical trial risk, through contract protections, meaning that [Emergent] will highly likely recognize the majority of the $1.5B in revenue, irrespective of the clinical outcome of these trials,” Cantor Fitzgerald said.
https://www.fiercepharma.com/pharma/hey-investors-covid-19-vaccine-manufacturer-emergent-won-t-suffer-from-az-j-j-trial-holds

Dr. Zelenko's Protocols for Treating Covid-19

Prehospital Management of Covid-19
Zelenko Protocol
Dr. Vladimir Zelenko
Twitter: @zev_dr


Treatment Plan for Patients with symptoms of Covid-19

Fundamental Principles 

Treat patients based on clinical suspicion as soon as possible, preferably within the first 5 days of symptoms.  Perform PCR testing, but do not withhold treatment pending results.  


Risk Stratify Patient 

Low risk patient - Younger than 60, no comorbidities, and not toxic (i.e. no shortness of breath)
High risk patient - Older than 60, younger than 60 with comorbidities, or looks toxic


Treatment Options

Low risk patients 

1. Rest, oral fluids
2. OTC Quercetin 500mg  2 a day for 7 days with Vitamin C 1000mg once a day for 7 days or     

    OTC Epigallocatechin-gallate (EGCG) 400mg once a day for 7 days

3. Elemental Zinc 50mg once a day for 7 days

4. Close follow up with doctor


High risk patients

1. Rest, oral fluids

2. Elemental Zinc 50mg once a day for 5 to 7 days. 

3. Hydroxychloroquine (HCQ) 200mg twice a day for 5 to 7 days or 

    Quercetin 500mg (OTC) 3 a day for 7 days and Vit. C 1000mg once a day for 7 days or
    EGCG 400mg (OTC) twice a day for 7 days
.
4. Azithromycin 500mg once a day for 5 days or 

    doxycycline 100mg twice a day for 5 to 7 days


Additional treatment options.  Should be uniquely custom tailored for every patient.

1. Ivermectin 6mg twice a day for 1 day   

2. Budesonide 1mg/2cc solution via nebulizer twice a day for 7 days

3. Dexamethasone 6mg once a day for 5 to 7 days

4. Blood thinners  (i.e. Lovenox)

5. Home O2

6. Home IV fluids


IF POSSIBLE, KEEP PATIENTS OUT OF THE HOSPITAL 

Supporting documents can be found here:  


https://faculty.utrgv.edu/eleftherios.gkioulekas/zelenko/index.html


