This blog began in 2007, focusing on anthrax vaccine, and later expanded to other public health and political issues. The blog links to media reports, medical literature, official documents and other materials.
The CDC has just released information, in its MMWR Weekly Report, on the prescribing of hydroxychloroquine in March and April in the US. Approximately 500,000 prescriptions dispensed by retail pharmacies were "new," or dispensed to persons who had not received a previous prescription of the medication in the prior 12 months. These are presumed to have been in response to Covid-19. By April 30, there were 1,075,000 confirmed or probable Covid cases in the US. CDC's report has not examined how many of those receiving HCQ also tested positive for Covid. Nonetheless, it appears that a considerable number of Americans and their physicians saw value in using the drug to prevent or treat Covid, especially compared to the number of total known cases. Where are their voices now? Did the medication help? Hurt? The rest of the country is dying to know.
For those who are worried about the “harms" caused by hydroxychloroquine—have you taken it? Prescribed it for a family member with Covid? Prescribed it for probably 200+ patients over 2 decades? Studied the literature? Well, I have done all of these.
Here are 3 recent studies discounting the drug’s cardiac toxicity:
The true harms of HCQ appear to be no greater than for drugs like the OTC NSAIDS (ibuprofen, aleve). The excessive harms that have been claimed were pulled out of thin air, just like the Lancet’s Mehra/Desai/Surgisphere paper, for the same purpose. That purpose is propaganda. It is the responsibility of medical doctors to seek to distinguish between propaganda and fact.
This is not an intellectual exercise. We are talking about a pandemic that has crashed the world economy, caused famines, and governments show no signs that things are going to change any time soon. Soif there is a magic bulletor perhaps many (see lab data on repurposed drugs for coronaviruses) -- the bullets need to be used asap, and not withheld to make way forremdesivir(about 3000x more costly and also more dangerous (https://www.drugs.com/sfx/remdesivir-side-effects.html) andpoorly tested vaccines that use novel platformsand, if used under Emergency Use Authorizations, willwaivemanufacturer and government liability.
Pay attention to the pre-Covid literature vs the post-Covid literature on HCQ harms.
In 2007 the Oxford journal Rheumatology
https://pubmed.ncbi.nlm.nih.gov/17202178/ found: "Conclusion: PR interval, QTc interval and heart rate were not different from normal values. The rate of heart conduction disorders was similar to what is expected in the general population, and contrasted with prior results in CQ-treated patients. Our results add further evidence on the safety of HCQ compared with CQ.” [BTW, excessive or prolonged doses can cause damage that will not occur in those treated for Covid, briefly, with standard doses.]
From Expert Opinion on Drug Safety 2011:
https://pubmed.ncbi.nlm.nih.gov/21417950/: "Expert opinion: HCQ has been shown by numerous studies over the past 15 years to be efficacious in the treatment of autoimmune diseases, including systemic lupus erythematosus, discoid lupus erythematosus and rheumatoid arthritis. HCQ does not appear to be associated with any increased risk of congenital defects, spontaneous abortions, fetal death, prematurity or decreased numbers of live births in patients with autoimmune diseases. Therefore, in the author's opinion, HCQ is safe for the treatment of autoimmune diseases during pregnancy.”
But it is too dangerous for patients with Covid? Who is fooling who?
When tested in OUTPATIENTS (so the side effects of the drug are not confused with the clinical damage caused by Covid or other meds being used) the drug is safe, according to the second cardiotoxicity link I provided above:
https://www.medrxiv.org/content/10.1101/2020.07.16.20155531v2"Conclusion: Data from three outpatient COVID-19 trials demonstrated that gastrointestinal side effects were common but mild with the use of hydroxychloroquine, while serious side effects were rare. No deaths occurred related to hydroxychloroquine. Randomized clinical trials can safely investigate whether hydroxychloroquine is efficacious for COVID-19.”
The CDC informed the world several days ago that 94% of Americans who died from Covid-19 had other medical conditions. When many people said, 'Aha! That means the pandemic is mainly killing those who are already ill," the mass media and fact-checkers went to work to debunk them.
USA Today quickly claimed that people were saying the deaths weren't caused by Covid-19, and it was a conspiracy theory.
But what I was hearing was simply that Covid-19 was mainly striking down people who were not otherwise healthy. While they might be dying from Covid, most were already weakened by something else.
For 6% of the deaths, COVID-19 was the only cause mentioned. For deaths with conditions or causes in addition to COVID-19, on average, there were 2.6 additional conditions or causes per death. The number of deaths with each condition or cause is shown for all deaths and by age groups.
But it turns out Bloomberg wrote about the same stats from Italy back in May, and guess what? 96% of those who died had co-morbidities, also known as pre-existing conditions. Sixty per cent of those who died had 3 or more preexisting illnesses. And the average age at death was 80:
The article below I wrote 8 years ago, but it has relevance to today. I describe some of the tricks that were pulled when a pandemic vaccine was rushed into use in 2009, and how the agencies that rushed it covered their tracks over the next several years--Meryl
Remember the 2009 Swine Flu Pandemic? There were going to be a huge number of illnesses and deaths, but then it turned out the flu virus caused less severe disease than usual.
... some manufacturers have conducted advance studies using a so-called “mock-up” vaccine. Mock-up vaccines contain an active ingredient for an influenza virus that has not circulated recently in human populations and thus mimics the novelty of a pandemic virus.Such advance studies can greatly expedite regulatory approval.
The clinical trials on which approval was based involved more than 6,000 people for each vaccine, each of whom received a version which was basically the same as the one to be rolled out, but originally contained an avian flu (H5N1) strain – which had been expected to cause a pandemic –instead of H1N1.
And POOF! -- hundreds of millions of people received the new, untested vaccines.
Later came the bad news.
The epidemic was actually mild, and most of those affected had few if any symptoms.
The vaccines had been given late, when most of the epidemic had passed, and many vaccinated people were already immune. The vaccine probably had little impact on the pandemic.
The Council of Europe got into the act, investigating WHO and the provenance of the contracts to understand how billions of healthcare dollars were spent to buy and administer unnecessary vaccines.
Except CDC didn't find them; instead, it estimated them. What was the authors' conclusion?
Although no estimates of symptomatic case fatality ratios were available from Africa and southeast Asia, a disproportionate number of estimated pandemic deaths might have occurred in these regions.
Human infection with H1N1 has generally resulted in low mortality, although certain subgroups... have significantly higher risk of severe disease.
Let's examine the claim of vaccine safety during pregnancy.
In the US, the major birth defect rate is about 3%. In the Danish study cited, the major birth defect rate in offspring of women vaccinated during their first trimester was 5.45%. But in the Danish control group, the major birth defect rate was 4.54%.
The authors were able to dismiss the high birth defect rate by selecting a control group with a higher than expected rate, and by using groups small enough that the 0.91% increased rate in the vaccinated cohort was not statistically significant.
I imagine these are only the first volleys in CDC's attempt to rewrite the history of swine flu and its vaccine, and justify its vaccine policies despite evidence to the contrary. Keep an eye out for what's next.
Many are afraid to take hydroxychloroquine (HCQ) for COVID as they have been told it could kill them because of its effect on the heart. Are you worried about this?
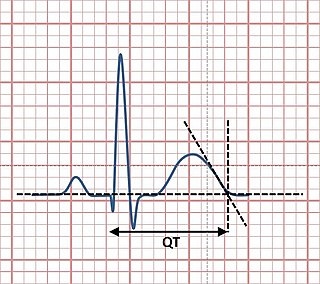
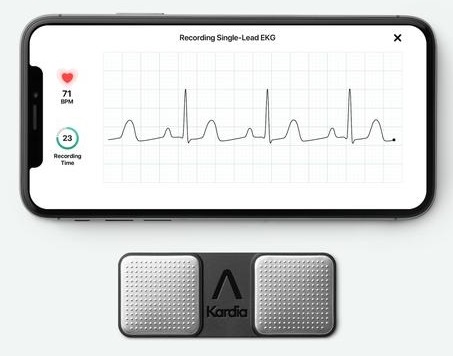
It is a fact that HCQ, azithromycin (Z-Pak™), and other drugs can prolong the QT interval on the electrocardiogram (ECG)—see image below. This could make patients vulnerable to fatal changes in the heart’s rhythm (such as torsades de pointes or TdP). People with a rare condition called “congenital prolonged QT syndrome” are especially at risk.You do not have to have an expensive ECG to check for this. It takes about 5 minutes with inexpensive new technology that fits in your pocket and can be used in your home (see below).Hundreds of millions of people have taken HCQ without ever worrying about this issue. Have we overlooked a serious problem for more than 50 years? A just-published article that reviews the medical literature concludes that, on the contrary, HCQ protects the heart.
In one case series of 251 COVID-19 patients treated with HCQ and azithromycin, extreme QT prolongation occurred in 23 percent. The HCQ was stopped; no deaths occurred. No reports of cardiac deaths were found in the review. Rather, “HCQ/azithromycin were uniformly found to substantially reduce cardiac mortality and also to decrease thrombosis, arrhythmia and cholesterol in treated patients.”
Warnings issued by FDA, CDC, the American Heart Association, and others have suppressed the use of potentially life-saving HCQ treatment. However, author Chadwick Prodromos, M.D., notes that warnings cite no specific study, and do not comment on whether actual deaths have occurred.He concludes that: “HCQ decreases cardiac events. HCQ should not be restricted in use for COVID 19 patients because of fear of cardiac mortality.”
It is important to remember that COVID-19 itself can damage the heart, increasing the importance of early treatment.
Cardiologist Peter McCullough, M.D., M.P.H., of the Baylor Heart and Vascular Institute in Dallas, recommends HCQ and other measures for early treatment in a recent article in the American Journal of Medicine.
I wrote this article in August, eleven years ago. The take-home lesson is that everyone having anything to do with a pandemic vaccine or drug program has had their product liability waived... as long as they don't know there are product defects. This incentivizes manufacturers to avoid testing products and fails to penalize them for selling shoddy or deadly pharmaceuticals. Please note that the links are 11 years old, and that there have been revisions to the laws I cited then, but generally the laws continue to provide broad immunity to all involved. Furthermore, a recent modification provides the same immunity to pharmacists and their staffs, who may now vaccinate children with any licensed vaccine or one authorized via an EUA. Note also that an additional Act regarding medical countermeasures and emergencies, PAHPRA was passed in 2013, so is not addressed in this 2009 article. The 21st Century Cures Act, passed in 2016 also has some relevant passages, including the fact that all vaccines recommended by CDC in pregnancy get a waiver of liability--Meryl
1. The US government is using laws designed for dealing with a very deadly pandemic, or bioterrorism, to bring about a mass vaccination program for swine flu, beginning with the Public Readiness and Emergency Preparedness Act 0f 2006.
2. This law removes liability from the manufacturer, medical practitioners who use the product, and from "government program planners" who decided on using the law. A suit can only be brought if the DHHS Secretary allows it, and if there is willful misconduct on the part of the manufacturer.
This law has been invoked for swine flu drugs (Tamiflu and Relenza),
3. If testing of these products is very limited, then the manufacturers are unlikely to become aware of their flaws, and specifically their adverse effects. Then there can be no willful misconduct.
4. Due to the fear that swine flu will cause a large outbreak once students return to schools, where the virus might rapidly spread, the US government has stated that vaccine is likely to be available, and used, before clinical trials are completed.
WHO says vaccine will be ready in September. Novartis began testing in humans in July, and Sanofi-Aventis and Glaxo Smith Kline are starting now.
5. The adjuvants likely to be used to strengthen vaccines and stretch the supply are named MF59 (Novartis) and ASO3 (Glaxo Smith Kline). Only 3 vaccines using this type of adjuvant (oil-in-water, a.k.a. squalene-containing) have been licensed in Europe, and none have been given a license in the US. Two vaccines using these adjuvants are only used in people above the age of 65 (Fluad-MF59), and those with serious kidney disease (Fendrix-ASO4). Both advanced age and kidney failure weaken the immune system, so more powerful vaccines are needed, but in this population autoimmunity is unlikely to result from powerful immune stimulation. Cervarix is the third European vaccine (using adjuvant ASO4 against HPV) and its safety is controversial.
6. The then-Acting DHHS Secretary issued an Emergency Declaration in response to the swine flu epidemic on April 26, 2009. This allows use of unapproved (unlicensed) medical treatments and tests, or use of approved treatments for unapproved uses.
7. Vaccines containing MF59 and ASO3 have not had Emergency Use Authorizations issued for them--yet. However, the government has purchased $698 million dollars' worth of these adjuvants in recent weeks.
US and WHO officials have indicated the likelihood of their use, which is the only way to achieve adequate amounts of vaccine for the US and world population in the fall.
8. These vaccines have never been demonstrated to be safe in children, pregnant women or young adults. They have not undergone comprehensive testing; for example, MF59 has not and will not be tested for carcinogenicity by the manufacturer.
9. The result of the new bioterrorism laws (passed with the expectation of use for much more dangerous epidemics than the current swine flu), which allow use of untested products AND give manufacturers an incentive to avoid comprehensive testing (to avoid being found guilty of willful misconduct) have combined with the political imperative to provide citizens with vaccines in a hurry, yielding a potential Perfect Storm.
In the 1976 swine flu vaccine program, 45 million people were vaccinated with an inadequately tested vaccine. The government gave the vaccine manufacturers immunity from liability, but created an alternative compensation program. Five thousand people sought benefits for vaccine injuries. Four hundred twenty seven developed the autoimmune, paralytic illness Guillain-Barre Syndrome. Over thirty of them died.
Postmarketing surveillance may be sufficient to identify severe side effects when new drugs are marketed, as they only gradually come to be used by large numbers of patients. But for a vaccine that will be employed in a mass inoculation campaign, targeted at half or more of the US population, tens (or hundreds) of millions will be vaccinated in a few weeks, before sufficient time has elapsed to learn about the adverse effects. Untested swine flu vaccines employing novel adjuvants, which are likely to cause more autoimmune illness than occurred in 1976, will almost certainly be used. The manufacturers have been given liability protection, as have the government program planners. Efficacy and safety are unknown. But no compensation mechanism has been created. And the public has not been informed.
"Belgium had one of the world’s worst [actually the worst recorded--Nass] per capita death rates this spring, with most of the mortality occurring in nursing homes. Now, even though cases have nearly quintupled compared to their lowest point in late June, Belgian hospitals remain calm. Very few cases are appearing in nursing homes, and 40 percent of new cases have been diagnosed among people between the age of 20 and 40....
Among European countries, Spain presents the most ominous picture. It is reporting nearly as many daily cases as it did in March, when it suffered as acutely as any country on the continent...The new cases have been detected largely among the young. Coronavirus hospitalizations, despite having quadrupled over the past month, remain manageable for the health system. In Madrid, 13.6 percent of hospital beds are occupied by coronavirus patients; in March the city’s hospitals were full.
In France, meanwhile, the government on Friday recorded a spike of 7,379 new cases in the past 24 hours — the second-largest single-day caseload since the pandemic began and the latest data point in an upward swing that began last month. Friday’s number was up more than a third from the already high figure posted just two days earlier... students return to class next Tuesday, masks in hand.
This protocol was developed by Dr. Paul Marik and additional colleagues over the past few months, and their results were published last week. They report a mortality rate of 5.1% in hospitalized Covid patients using the protocol, which notably does include zinc. Compared to other, historical data from hospitalized Covid patients, this is a 75% reduction in mortality. The protocol does not include HCQ, as I was told the protocol is intended for the late treatment of Covid, and since HCQ performs best in early treatment, its use might have muddied the waters regarding the benefits this (less controversial) treatment protocol provides. https://covid19criticalcare.com/math-hospital-treatment/scientific-review-of-covid-19-and-math-plus/#1596276202652-85a61317-47b4 The authors provide the evidence base for each component of this protocol:
Evidence based scientific reviews supporting MATH+ components:
Deaths and hospitalization rates are the two measures available to the US public to best assess Covid extent and severity.
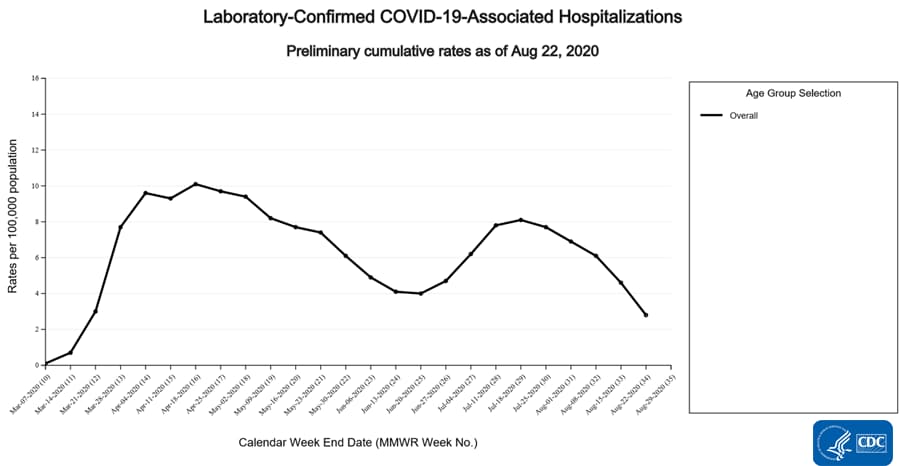
Hospitalization rates are definitely down; see CDC's graph below. Mortality rates have held steady at 1000/day for the whole of the past month.
I have no data on how treatment patterns have changed over time in the US, except that ventilator use for Covid is uncommon now. US hospitalization rates for Covid are now half what they were during the second peak in July.
Per CDC: Weekly hospitalization rates among all ages first peaked during the week ending April 18 (MMWR week 16) at 10.1 per 100,000 population, followed by a second peak during the week ending July 18 (MMWR week 29) at 8.0 per 100,000 population. Data for the most recent weeks may change as additional admissions occurring during those weeks are reported.
I have been criticized by USAToday and 6 other fact-checking sites over the past few days (since Plandem!c 2: Indoctornation came out). In the film, I say I believe the coronavirus came from a lab. The fact-checkers:
a) claim scientific consensus that the virus had a natural origin. But there is no consensus. For example, a WHO spokesperson told USAT, "It is probable, likely, that the virus is of animal origin" and just last week Pro Publicawrote, "the origins of COVID-19, which has killed more than 775,000 people worldwide and infected 21.7 million others, continue to elude public health officials and other investigators."
b) criticize me for not explaining the basis for my opinion.
The single scientific paper cited by the 7 fact-checkers to dispute me was a commentary written by 5 scientists with sketchy backgrounds whose argument I dissected in March. So did my colleague Ed Hooper here, and many others have, as well.
Below is a quick summary of my position regarding that paper, from an interview I did with Kevin Barrett, PhD in April. The argument is expanded in my interviews with Dr. Mercola and an AMA on Reddit regarding the SARS-CoV-2 furin cleavage site and unique spike protein, which is highly adapted to humans but not to bats, suggesting passage through human cells before it entered the human population. Yuri Deigin has the best review I've seen of the origin subject here, and I recommend that everyone with interest in the question of the virus' origin read it.
Here is a part of the Kevin Barrett-Meryl Nass interview:
Why are five dubious, germ-warfare-linked, cover-up specialist scientists telling us this could not possibly be a bioweapon, and yet obviously it could?
Meryl Nass: “Well, that’s the $64,000 question, isn’t it? …The Cubans blame (the first author [of a Lancet letter that insisted questioning the virus's origin would result in conspiracy theories that would damage the response to Covid]) who worked for a federal agency for their Dengue outbreak…I knew of several of the Nature Medicine authors…and they too were sort of biological defense, biological warfare people. Well, let me just say two of them I would call spooks with Ph.Ds, who have come out and done research on a whole very odd collection of subjects, all of which the US government has tried to cover up…And so these five scientists wrote a piece in Nature Medicinewhich claimed to have found the scientific linchpin to be able to make the argument that the new coronavirus is a natural occurrence. And the argument they made was that had it been constructed in the lab, it would have used the particular backbone that laboratorians know about. But because it didn’t have that backbone, it couldn’t possibly be a lab construct.
“The problem with that argument is basically it was a straw man argument. They said, well, if I were going to make the novel coronavirus, I would have made it this way, but because it isn’t made that way, it’s not a lab construct. Of course, you can make the novel coronavirus a lot of different ways. And I pointed out three different ways one might have come up with a novel coronavirus that weren’t using the method they suggested…my study of biological warfare, which has extended over decades, (shows) that the biological warfare warrior never chooses an (obvious) weapon. They always require plausible deniability…
“…It’s ridiculous to claim that only if you used an easily discoverable method of producing a biological weapon would it be successful; or you wouldn’t have done it any other way. I mean, it’s such a simplistic argument.
You wonder, couldn’t they have come up with a better argument? Is that all they’re left with? Because any scientist could see through it in a moment.”
TUCSON, Ariz., Aug. 20, 2020 (GLOBE NEWSWIRE) -- Senator Ron Johnson (R-Wis.), Chairman of the Homeland Security and Governmental Affairs Committee, along with Sen. Mike Lee (R-Utah) and Sen. Ted Cruz (R-Texas), in a letter to Food and Drug Administration (FDA) Commissioner Stephen Hahn, write that “the FDA’s actions regarding [hydroxychloroquine] HCQ may be directly costing lives by limiting outpatient access to this potentially beneficial treatment.”
On May 29, Dr. Hahn stated: “Prescribing a product for uses not specifically included in the official labeling is common in the practice of medicine. In oncology and mental health, many patients are treated this way.”
He notes that with COVID-19 “health care professionals are looking for every possible treatment option for their patients,” and that patients and their doctors “must ultimately decide what treatment is likely to be best for the individual patient.”
Dr. Hahn recognizes that “hydroxychloroquine and chloroquine have received particular attention. Both are FDA-approved to treat or prevent malaria, and hydroxychloroquine is also approved to treat autoimmune conditions such as chronic discoid lupus erythematosus, systemic lupus erythematosus in adults, and rheumatoid arthritis. They have been prescribed for years to help patients with these debilitating, or even deadly, diseases and have a well-established safety profile for these conditions.”
Despite these statements, the senators write that FDA’s actions on HCQ have “led to misinformation and confusion across the country. Some states have restricted the ability of physicians to write and pharmacies to fill HCQ and CQ prescriptions.”
The senators ask the FDA to provide the Committee, by Aug 25, with all information pertaining to FDA decisions that discourage the outpatient use of HCQ for early treatment or prophylaxis of COVID-19, and also “any public statements or records that FDA has issued to clarify that the FDA does not regulate the practice of medicine and that state governments may not regulate the sale or prohibit the sale of prescription drugs.”
“The licensed physicians we have heard from… have pointed to the low mortality rates in other countries—like India, Turkey, South Korea, and Morocco—that are using HCQ widely on outpatient COVID-19 populations before the disease progresses to more lethal stages of the virus that require hospitalization.”
The senators conclude: “Physicians taking care of patients in our communities across the country must be free to make the best medical and treatment decisions for their patients, use their ‘off label’ prescription rights, and have full access to FDA approved drugs.”
AAPS has represented physicians of all specialties in all states since 1943. The AAPS motto is omnia pro aegroto, meaning everything for the patient.
Contact: Jane M. Orient, M.D., (520) 323-3110, janeorientmd@gmail.com
If you were trying to watch the documentary Plandemic 2: Indoctornation after someone sent you a link on Facebook, you probably found it impossible. According to Forbes,
Users who attempted to share the link were met with a warning message stating the URL to the video goes against Facebook’s community guidelines because it contained “COVID-19 claims that our fact-checking partners have repeatedly rated false.”
Yesterday I received a phone call from FactCheck.org demanding I answer a myriad of questions about the facts and opinions I expressed in the documentary Plandemic 2: Indoctornation, which had been released hours earlier. I referred the caller to my blog posts for documentation supporting what I had said. I then looked up Factcheck.org's funding, most of which came from Facebook and Google during the past year ($423,745) and past quarter ($187,265).
It seems that those who "check" the "facts" did not actually check any facts, because they were all working off the identical script, which they dutifully regurgitated, to smear me and the film. Who gave them all the same talking points, which were outdated and fail to acknowledge the current controversy among scientists, intel professionals and others regarding the provenance of the SARS-2 virus?
Politics406, AFP, checkyourfact, healthfeedback, TechTimes, Factcheck and Politifact all reference the exact same March article in Nature Medicine (that I and othersdebunked at the time), which claimed to prove SARS-CoV-2 came from a bat. The NatureMed authors used a straw man argument that essentially said, if we were going to design a lethal coronavirus, we would have done it this way. But it wasn't done that way, so it came from a bat and not a lab. Please ignore the fact we have been unable to find a similar virus in bats, and we certainly cannot explain why this virus is so much better adapted to humans than bats. Trust us anyway. This is the best argument that can be made for a natural origin? Yet it has been used to ban my appearance, the film Plandemic 2, and discussion of the film from many platforms.
The linkCheckyourfact uses to claim scientific consensus, in fact discusses the scientific disagreement on the origin of the virus. And while the Office of the Director of National Intelligence said at one time it believed the virus came from nature, it backtracked shortly afterward, raising the possibility it came from a lab. Sir Richard Dearlove (former head of Britain's MI6) raised the lab hypothesis in the same story Checkyourfact linked to, to support its claim of consensus regarding the natural origin theory. Fact checkers don't have enough time to check their own facts apparently.
Who gave all these so-called fact-checking sites the identical set of talking points? And could this level of coordination be evidence of a conspiracy to suppress the film and smear those appearing in it? How is it that such shoddy fact-checking by "partners" is sufficient to ban and shadowban the film in most major outlets, including Facebook and Reddit?
UPDATE: A tweet from Professor Richard Ebright from February was used as evidence against a lab origin in one of the fact-check articles. Professor Ebright has since clarified his opinion that the virus could have come from a lab with the following:
"Professor Richard Ebright of the Waksman Institute of Microbiology at Rutgers University in New Jersey was dismissive of the Dalgleish-Sorensen paper but he took issue with Professor Andersen's piece in Nature too, describing it as opinion.
"The op-ed's conclusion that SARS-CoV-2 genome shows no signatures of purposeful human manipulation is correct," he said in an email exchange. [Professor Ebright is referring to the article I challenged in March and April, which was mentioned by every one of the fact-check pieces to claim I was wrong.--Nass] "The absence of signatures rules out the possibility the virus was engineered using methods that leave signatures. However, the absence of signatures of manipulation does not rule out the possibility the virus was engineered using widely employed - including at WIV - methods that do not leave signatures. The op-ed does not even address the possibility that an unpublished WIV bat coronavirus… could be the progenitor of SARS-CoV-2."
UPDATE: Just in case you still do not think there is a conspiracy to suppress the documentary, here is what Politifact wrote:
Soon after the live feed started, Facebook blocked its users from sharing the link in posts and private messages. TikTok appeared to block searches for the term "Plandemic." Twitter added a warning message saying the link is "potentially spammy or unsafe." Still, according to CrowdTangle, a social media insights tool, Facebook and Instagram posts with the term "Plandemic" have received tens of thousands of combined interactions since Aug. 17...
Tens of millions of people saw the shorter [Plandemic] video before social media platforms removed it for violating their policies against harmful COVID-19 misinformation. This version hasn’t received as many views, because the tech platforms were expecting it.
Politifact is owned by the Poynter Foundation. While Poynter claims to share its tax returns, the section of the return where contributors must be listed is blank. Poynter does acknowledge Facebook having contributed over 5% of revenue elsewhere on its website. Update: On August 23 USAToday factcheck uses the identical argument as the 6 fact-check sites to insist on a natural origin of coronavirus, citing the Nature Medicine commentary and the Lancet letter, both of which I debunked in March and April. Like the 6 sites, USAT criticizes me for not explaining in the film the reasons I think the virus came from a lab. Never mind that I have provided those reasons at length in my blog hereherehere herehereherehere and here (using USAT as the source for the last post), and gave that information to the single fact-checker who called me. My reasoning, which all 7 of these organizations criticized me for not providing, is certainly not hiding, and has been detailed by me for the past 5 months.
I am a board-certified internal medicine physician. I have given 6 Congressional testimonies and testified for legislatures in Maine, Massachusetts, Vermont, New Hampshire, Alaska, Colorado and New Brunswick, Canada on bioterrorism, Gulf War syndrome and vaccine safety/vaccine mandates. I have consulted for the World Bank, the Government Accountability Office, the Cuban Ministry of Health and the US Director of National Intelligence regarding the prevention, investigation and mitigation of chemical and biological warfare and pandemics.
I was the first person in the world to investigate an outbreak and prove it was due to biological warfare, publishing the results in 1992. This was the world’s largest anthrax outbreak, which occurred during Rhodesia’s civil war. I was a main author, along with Robert F Kennedy Jr. and the NGO Childrens Health Defense, of a Citizen’s Petition to the FDA regarding the Covid vaccines' authorizations and their single approval, and a letter to the FDA and its vaccine advisory committee regarding the many reasons the vaccines are not suitable for children.
I am also the author of detailed articles regarding the suppression of hydroxychloroquine and ivermectin for treatment of Covid, which have been read by over 50,000 people on my website, and been reprinted on many other sites. I have been interviewed by all major US newspapers, TV networks, and numerous alternative channels.
Meryl and other panelists at Anthrax Letters seminar, Washington, D.C., November 29, 2010
Meryl, enjoying spotting animals in the Thai jungle
Visiting tigers (inside the cages) in Chiang Mai
I think I'm in the wrong cage...
Night shot of a wild elephant
Canoodling at Elephant Nature Camp, Thailand
5 and 7 month olds playing
Mum and her 5 month old infant
Dusky Langur, curious about us humans in his territory
Self-satisfied Dusky Langur, after he relieved himself on me
Rhesus macaque: "I need three hands for this meal"
After swimming with dolphins at Key Largo, they checked me out at the edge of the pool
Visiting a Bhutanese Dzong, the regional seat of both government and religion (and a fort for good measure)
Why am I blogging?
Because life is meant to be lived! The left side of this blog has photos of some peak experiences. And the right side contains information about which I am passionate.
Too many peoples' lives are characterized by lack of authenticity, and fear of acknowledging and expressing their true nature. Employees cannot say what they think at work, and in the corporate system we must squish ourselves into square holes when we are round pegs. We thus lose touch with our souls, becoming cogs in a soulless, profit-driven machine.
The culture of political correctness has meant, in medicine, that we ignore how the foundations of our science are being undermined by commercialism. Clinical data generated or presented by the manufacturers of drugs, vaccines and devices cannot be trusted: there are hundreds of studies proving this. But this fraudulent information continues to be the only data informing the approval of vaccines, drugs and devices.
Unless scrupulous ethical conduct is demanded of physicians and biological scientists, our lack of meaningful standards will carry the medical-pharmaceutical system down the path of increasing irrelevance.
Medicine and its tools need to be affordable. The current medical-industrial milieu, characterized by contempt for science, countless ways for insiders to achieve wealth due to failure of good governance, and regulatory agency-to-industry revolving doors, has ushered in stratospheric pricing... further kicking us down that path to irrelevance.
Why is our new health care plan a giveaway to health industries instead of to health consumers? Why won't it cover all Americans? Why was the "public option" never an option for the Obama administration? Why did the promised Trump health plan evaporate the moment he was elected?
So many of our leaders carry a heavy burden of mendacity and avarice. If they instead got in touch with their own souls (perhaps by exposure to the natural world), or made their decisions by maximizing the amount of good that results, our leaders might find real meaning and value in their lives.
Until that happens, the only way to straighten out the current mess is to demand accountability and impose penalties on unethical/dishonest leaders. Both political parties enjoy bounteous hors d'oeuvres from Pharma's table, making it unlikely the existing political "process" will provide relief--as we've seen in the demoralizing healthcare reform drama.
Until then, I'll continue to "call it as I see it" in this blog -- working and living the way life should be, in rural Maine, far from the centers of power.
Ellen Byrne has created several designs encapsulating aspects of the FBI's ridiculous case against Bruce Ivins. They can be purchased on T-shirts and coffee mugs. All proceeds will be donated to the the Frederick County chapter of the American Red Cross, a favored charity of Dr. Bruce Ivins.