Sunday, November 29, 2015

Obama's Stake in the Heart to the Inspector General system at 70 federal agencies: "No records for you!"

Just in case you still think the US government has a functioning system of checks and balances, the following article in yesterday's NY Times' by Eric Lichtblau should disabuse you of such a quaint notion.

As the article explains, the Inspector General (IG) watchdog system was instituted in the wake of Watergate to provide independent oversight of 72 agencies in the executive branch of government:  i.e., so the President cannot become the Emperor, and secret operations would not be conducted by the agencies, because they could be unmasked.  

Other Presidents chafed under the IG regimen; Reagan fired 15 IGs. But Obama has thrown the biggest wrench in the works so far, advising agencies to "Just Say No" when the IGs ask for agency records to learn what the agencies they oversee are doing.

The ramifications are huge.  What can be done with a 3.8 trillion dollar federal budget when no one is looking? Here is the piece in full:

 
WASHINGTON — Justice Department watchdogs ran into an unexpected roadblock last year when they began examining the role of federal drug agents in the fatal shootings of unarmed civilians during raids in Honduras.
The continuing Honduran inquiry is one of at least 20 investigations across the government that have been slowed, stymied or sometimes closed because of a long-simmering dispute between the Obama administration and its own watchdogs over the shrinking access of inspectors general to confidential records, according to records and interviews.
The impasse has hampered investigations into an array of programs and abuse reports — from allegations of sexual assaults in the Peace Corps to the F.B.I.’s terrorism powers, officials said. And it has threatened to roll back more than three decades of policy giving the watchdogs unfettered access to “all records” in their investigations.
“The bottom line is that we’re no longer independent,” Michael E. Horowitz, the Justice Department inspector general, said in an interview.
The restrictions reflect a broader effort by the Obama administration to prevent unauthorized disclosures of sensitive information — at the expense, some watchdogs insist, of government oversight.
Justice Department lawyers concluded in a legal opinion this summer that some protected records, like grand jury transcripts, wiretap intercepts and financial credit reports, could be kept off limits to government investigators. The administration insists there is no intention of curtailing investigations, but both Democrats and Republicans in Congress have expressed alarm and are promising to restore full access to the watchdogs.
The new restrictions grew out of a five-year-old dispute within the Justice Department. After a series of scathing reports by Glenn Fine, then the Justice Department inspector general, on F.B.I. abuses in counterterrorism programs, F.B.I. lawyers began asserting in 2010 that he could no longer have access to certain confidential records because they were legally protected.
That led to a series of high-level Justice Department reviews, a new procedure for reviewing records requests and, ultimately, a formal opinion in July from the department’s Office of Legal Counsel. That opinion, which applies to federal agencies across the government, concluded that the 1978 law giving an inspector general access to “all records” in investigations did not necessarily mean all records when it came to material like wiretap intercepts and grand jury reports.
The inspector-general system was created in 1978 in the wake of Watergate as an independent check on government abuse, and it has grown to include watchdogs at 72 federal agencies. Their investigations have produced thousands of often searing public reports on everything from secret terrorism programs and disaster responses to boondoggles like a lavish government conference in Las Vegas in 2010 that featured a clown and a mind reader.
Not surprisingly, tensions are common between the watchdogs and the officials they investigate. President Ronald Reagan, in fact, fired 15 inspectors general in 1981. But a number of scholars and investigators said the restrictions imposed by the Obama administration reflect a new level of acrimony.
“This is by far the most aggressive assault on the inspector general concept since the beginning,” said Paul Light, a New York University professor who has studied the system. “It’s the complete evisceration of the concept. You might as well fold them down. They’ve become defanged.”
While President Obama has boasted of running “the most transparent administration in history,” some watchdogs say the clampdown has scaled back scrutiny of government programs.
“This runs against transparency,” said the Peace Corps inspector general, Kathy Buller.
At the Peace Corps, her office began running into problems two years ago in an investigation into the agency’s handling of allegations of sexual assaults against overseas volunteers. Congress mandated a review after a volunteer in Benin was murdered in 2009; several dozen volunteers reported that the Peace Corps ignored or mishandled sexual abuse claims.
But Peace Corps lawyers initially refused to turn over abuse reports, citing privacy restrictions. Even after reaching an agreement opening up some material, Ms. Buller said investigators have been able to get records that are heavily redacted.
“It’s been incredibly frustrating,” she said. “We have spent so much time and energy arguing with the agency over this issue.”
The Peace Corps said in a statement, however, that it was committed to “rigorous oversight” and has cooperated fully with the inspector general.
Agencies facing investigations are now sometimes relying on the Justice Department’s opinion as justification for denying records — even records that are not specifically covered in the opinion, officials said.
At the Commerce Department, the inspector general this year shut down an internal audit of enforcement of international trade agreements because the department’s lawyers, citing the Justice Department’s guidance, refused to turn over business records that they said were “proprietary” and protected.
The Environmental Protection Agency’s inspector general has reported a series of struggles with the organization over its access to documents, including records the agency said were classified or covered by attorney-client privilege. And investigators at the Postal Service, a special Afghanistan reconstruction board, and other federal agencies have complained of tightened restrictions on investigative records as well.
Hopes of a quick end to the impasse have dimmed in recent days after the Obama administration volunteered to restore full access for the Justice Department’s inspector general — but not the other 71 watchdogs.
Attorney General Loretta E. Lynch, asked about the issue at a House hearing last week, said the proposal was intended to ensure, at least at the Justice Department, “that the inspector general would receive all the information he needed.”
 “It’s no fix at all,” said Senator Charles E. Grassley, Republican of Iowa, who leads the Judiciary Committee.
In a rare show of bipartisanship, the administration has drawn scorn from Democrats and Republicans. The Obama administration’s stance has “blocked what was once a free flow of information” to the watchdogs, Senator Patrick J. Leahy of Vermont, the ranking Democrat on the Judiciary Committee, said at a hearing.
A Justice Department spokeswoman, Emily Pierce, said in a statement on Friday: “Justice Department leadership has issued policy guidance to ensure that our inspector general gets the documents he requests as quickly as possible, even when those documents are protected by other statutes protecting sensitive information. The department is unaware of any instance in which the inspector general has sought access to documents or information protected from disclosure by statute and did not receive them.”
Nowhere has the fallout over the dispute been felt more acutely than at the Justice Department, where the inspector general’s office said 14 investigations had been hindered by the restricted access.
These include investigations into the F.B.I.’s use of phone records collected by the National Security Agency, the government’s sharing of intelligence information before the 2013 Boston Marathon bombings, a notorious gun-tracing operation known as “Fast and Furious” and the deadly Honduran drug raids.
In the case of the Honduran raids, the inspector general has been trying to piece together the exact role of D.E.A. agents in participating in, or even leading, a series of controversial drug raids there beginning in 2011.
Details of what happened remain sketchy even today, but drug agents in a helicopter in 2012 reportedly killed four unarmed villagers in a boat, including a pregnant woman and a 14-year-old boy, during a raid on suspected drug smugglers in northeastern Honduras. They also shot down several private planes — suspected of carrying drugs — in possible violation of international law.
An investigation by the Honduran government cleared American agents of responsibility. But when the inspector general began examining the case last year, D.E.A. officials refused to turn over emails on the episodes from senior executives, the inspector general’s office said. Only after more than 11 months of back-and-forth negotiations were all the records turned over.
The D.E.A. refused to comment on the case, citing the investigation. A senior Justice Department official, speaking on the condition of anonymity because of the continuing review, said the refusal to turn over the records was the flawed result of “a culture within the D.E.A.” at the time — and not the result of the Justice Department’s new legal restrictions.
Mr. Horowitz, the inspector general, said the long delay was a significant setback to his investigation. He now hopes to complete the Honduran review early next year.
In the meantime, the watchdogs say they are looking to Congress to intervene in a dispute with the administration that has become increasingly messy.
“It’s essential to enshrine in the law that the inspector general has access to all agency records,” said Mr. Fine, who is now the Pentagon’s principal deputy inspector general. “The underlying principle is key: To be an effective inspector general, you need the right to receive timely access to all agency records.”

Thursday, October 22, 2015

How Good is a Flu Shot? Likely 1-3% chance it will prevent you from getting influenza this year/Lown Institute Blog

Written by Alan Cassels, a British Columbia drug policy researcher, via Lown Institute Weekly:
“Normally, the flu vaccine is between 50 to 60 percent effective”— Dr. Tom Frieden, Director of the Centers for Disease Control and Prevention (CDC)
How effective is the flu shot?   
That’s an important question that generates many headlines across North America every fall as the public health community starts ramping up its fall flu campaigns. Problem is, the media tends to generate a lot of noise around that number, but provide very little clarity.
Influenza stories this time of year swirl around similar themes, often with the CDC taking center stage (featuring the platitudinous photo op of the CDC director rolling up his sleeve for the shot), including the importance of the flu shot, the need for general hand hygiene and the expected effectiveness of the vaccine this year.
The number that arrives as predictably as the fall flu campaign is “60” as in this storythat repeats the mantra: “Flu shots normally prevent 60% to 65% of infections serious enough for people to see a doctor.” Across North America, public health officers will stress that the flu vaccine “reduces the risk by 60%!” Sixty sounds good. Impressive. Powerful. But ultimately as meaningless as a used car salesman with big bright signs of “60% off” plastered on every car on the lot, without ever telling you what the regular prices are. Despite the potential for a huge bargain on that purchase, the reality is that you’re in for a much smaller deal than you think you are. MUCH smaller.
And so it goes with the flu shot. When people hear “60% reduction,” I believe this is what happens inside their thought bubble: “If my risk of getting the flu this winter is 100%, the shot will reduce that to 40%. So instead of 100 people getting the flu, only 40 would get it. Hmmm. This 60% reduction sounds like great odds.”   
Even when the flu vaccine seems less effective, like in this story which said that “last year the flu shot, by the CDC’s own numbers, was 23% effective,” people might think it’s a good deal. 23% off that Chevy Impala in the back lot might be a great bargain. But what does the 23% or 60% really mean?  
Since they are relative numbers, they demand us to ask “23% of what?” or “60% of what?”  As we’ve made abundantly clear at HealthNewsReview.org, using relative numbers on their own are a statistical no-no because, to quote ourselves, “we think the relative risk number tends to inflate the impression of how much impact the drug [or vaccine] has.” For a quick refresher on relative numbers check out our review criteria here.
I find the 60 or the 23 percents irritating, not to mention epically misleading and I’m not alone. One commentator looking at a flu study reporting a “24% risk reduction” called it “Cockamamie propaganda”. Colorful but true.  
To get some perspective I talked to Dr. Tom Jefferson in Rome who has reviewed hundreds of flu vaccine studies as part of the Cochrane Collaboration. Dr. Jefferson gives me a quick tutorial on the 60% which he calls “CDC / pharma spin of the worst kind.”
He reminded me that every flu season there are over 200 viruses which can cause influenza and influenza-like illness, all perfectly capable of making you headachy and feverish. Most people get through the flu just fine and, thankfully, the risk of death or serious illness in otherwise healthy people is rare. In a good year the vaccine might protect you against influenza A and B, which might make up about one tenth of all circulating viruses.
The best way to assess flu trials is to look at those that compared vaccinated people with unvaccinated people.  
When Jefferson and his colleagues published their March 2014 review they found that under ideal conditions (when the vaccine matches the main viruses circulating that season) you need to vaccinate 33 healthy adults to avoid one set of influenza symptoms. This is what we’d call a NNV (Numbers needed to Vaccinate) of 33. When the vaccine match isn’t so good as it was last year, the NNV is about 100. That is, of 100 people vaccinated, 99 will have no benefit and one person will avoid one set of influenza symptoms. Vaccination did not seem to affect the number of people hospitalised or who lost working days.     
Almost half (15 of the 36 trials they examined) were funded by vaccine companies and four had no funding declaration. His team cautioned that even these numbers may represent an “optimistic estimate” because “company-sponsored influenza vaccines trials tend to produce results favorable to their products.” You can read more details here.
As for the magical “60?” Dr. Tom Jefferson didn’t mince words: “Sorry I have no idea where the 60% comes from – it’s either pure propaganda or bandied about by people who do not understand epidemiology. In both cases they should not be making policy as they do not know what they are talking about,” he said, insisting that I quote him.
When asked to explain the 60% number via email, the CDC sent me a link to their website, which states that the 60% figure is a “point estimate” of laboratory-confirmed flu illness that results in a doctor’s visit or urgent care visit, presumably derived from studies such as this one showing a “61%” effectiveness rate for the 2013/2014 shot.
If you don’t go beyond the “60%” headlines, you probably wouldn’t question the vaccine because if A) the vaccine is so effective, B) the vaccine is ‘free’ or almost free; and C) it’s relatively safe, then how could you say no to that?
Doesn’t that equation change if the effectiveness is between 1 to 3 percent, depending on how well this season’s circulating virus has been matched with the new vaccines? 
As the CDC continues to stress that “a yearly flu vaccination is still the best protection currently available against the flu,” you can imagine the confusion playing out in the thought bubbles of the general population.  
What I long for—and I haven’t seen it yet—is for media coverage this season to start reporting on absolute differences related to the flu vaccine. I’d like to see how the “1-3% effectiveness of the vaccine” floats around in the public’s thought bubbles. How does that compare with something as simple as staying home and not infecting other people or washing your hands more frequently?
I think if the real numbers were out there, we might see a much broader public conversation about what other sorts of flu “protection” are worthwhile.

Saturday, October 3, 2015

WaPo Claims it is Too Dangerous for Presidential Candidates to Discuss the Vaccine Sacred Cow

Several Republican Presidential candidates (Donald Trump, Dr. Ben Carson and Dr. Rand Paul) were asked in the debate September 16 about their opinion of whether vaccines are linked to autism.  Trump said yes, vaccines cause autism.  He gave examples of his employees whose normal children regressed into autism shortly after a vaccination.

Dr. Ben Carson, a retired pediatric neurosurgeon, hedged.  Vaccines are good, but not always for everybody. Quoted in the WaPo, Carson said:
“Vaccines are very important,” Carson said, before qualifying: “Certain ones. The ones that would prevent death or crippling. There are others, there are a multitude of vaccines which probably don’t fit in that category, and there should be some discretion in those cases.”
Dr. Rand Paul, an ophthalmologist, is all for vaccines, "But I'm also for freedom." Both he and Trump think vaccines should be spread out.  Trump  wants "smaller doses over a longer period of time." Carson seemed to agree with this. "It is true that we are probably giving way too many in too short a period of time," he said. "And a lot of pediatricians now recognize that, and, I think, are cutting down on the number and the proximity in which those are done, and I think that's appropriate."

CBS has posted video and transcribed this part of the vaccine debate.

Stop the presses.  Three Presidential candidates (2 who are MDs) share the view that too many vaccines are given too close together.  Not every vaccine needs to be forced on every child.  Yet they like vaccines.  They feel they could be used more wisely.

I share this opinion, as do tens (or hundreds) of millions of Americans.

But the Washington Post published a hatchet piece criticizing the three candidates' answers. The WaPo piece was titled "GOP's dangerous 'debate' on vaccines and autism."  Wow.  A subject too dangerous to debate.  Really?  Why is this discussion dangerous?

Because WaPo, mainstream media and the nanny state are intent on controlling the vaccine debate.  They want the debate limited to two positions only:  CDC staff and hand-picked "experts" who favor one-size-fits-all vaccine mandates, on the one hand, and the ignorant "crazies" who are against all vaccines for everyone, on the other.

The media (and especially the WaPo) are doing their darnedest to pretend the reasonable middle ground in the vaccine debate does not exist. In this case, they are trying to silence three Presidential candidates, two of whom happen to be physicians and probably more knowledgeable than WaPo journalist Michael Miller.

The media have created a straw man: a self-indulgent, anti-science, anti-vaccine caricature that the media can disparage and destroy. It has to be all or nothing:  you favor forcing every child to receive every government-designated vaccine that is added to the schedule by CDC, or you hate vaccines, period. Reasonable facts and and opinions will not be allowed in this debate. Freedom to pick and choose your vaccines, when you deem they are desirable--which until recently was the norm--has become anathema.  Such ideas are too dangerous.  Better to deny them any hint of legitimacy and definitely no prime time. Reporter Sharyl Atkisson recently wrote about how the media ignore or demean substantial scientific evidence linking vaccines to neurologic injuries and autism.

But now three Presidential candidates have carved out similar turf:  talking about a more reasoned vaccine policy.  Presumably they don't think their opinions will be as problematic for the voters as they are for the Post.  Here's why.  Despite the CDC/media mantra that all vaccines are safe, the public has doubts.

A significant minority of Americans think that vaccines may have something to do with autism, or other neurologic impairments in children.  A 2011 Harris poll discussed in USNews found that only 52% of Americans were sure vaccines did not cause autism.  The rest of us are not so sure...

The American Academy of Pediatrics (AAP) inserted itself into the Republican debate, tweeting shortly after the broadcast:  "Vaccines are safe. Vaccines are effective. Vaccines save lives."  Well, AAP, you may represent the pediatricians of America, but it is high time you learned that vaccines are drugs--according to FDA--and all drugs are safe to a degree, effective to a degree, and kill some people, sometimes.  If all were safe all the time, why would we need doctors to prescribe them?  AAP, be careful you don't tweet yourself out of a job.

UPDATE:  I forgot that in order to increase vaccinations, pharmacists may now prescribe and immediately administer vaccines (via so-called "protocols"), even to children.  In 39 states, pharmacy interns can administer vaccines.

The local pharmacist at a national chain told me she has a vaccination quota to meet. Doctors and hospitals have vaccine quotas too, when insurers like Medicare designate vaccination rates a "quality measure."

Was a vaccine recommended to you in order to meet the corporate/government quota?

US Airstrike bombs MSF hospital in Kunduz, Afghanistan relentlessly for an hour, despite knowing its location/ Reuters, NYT, Guardian

UPDATE:  From the Oct 11 WaPo:
The AC-130U plane, circling above in the dark, raked the medical compound with bursts of cannon fire, potentially even using high explosive incendiary munitions, for more than an hour. The assault left at least 22 people dead, some of them burned to death.
A US airstrike on Kuduz repeatedly strafed the MSF (Medicins Sans Frontieres or Doctors Without Borders) hospital in Kunduz, the only tertiary care hospital in the area--which treats the wounded from all sides--even after calls to US military HQ by MSF begging it to stop.  At least 19 medical staff and patients died, some from burns in the ensuing fires. The UN High Commissioner for Refugees said this may qualify as a war crime.

From the NY Times:
In a statement, the aid group accused the American military of continuing the bombing for 30 minutes after receiving phone calls telling military contacts that the hospital was being bombed.
“All parties to the conflict including in Kabul and Washington, were clearly informed of the precise location [GPS Coordinates] of the MSF facilities — hospital, guesthouse, office,” the statement said. “MSF urgently seeks clarity on exactly what took place and how this terrible event could have happened,” it said.
From Reuters:
Almost 200 patients and employees were in the hospital, the only one in the region that can deal with major injuries, said Medecins Sans Frontieres, which raised the death toll to at least 16 by late on Saturday.
"We are deeply shocked by the attack, the killing of our staff and patients and the heavy toll it has inflicted on healthcare in Kunduz," operations director Bart Janssens said in a statement.
MSF said it gave the location of the hospital to both Afghan and U.S. forces several times in the past few months, most recently this week, to avoid being caught in crossfire.
From The Guardian:
“Why did the US blow up the whole hospital?” said Nasratullah, whose 25-year old cousin Akbar was among the doctors killed. “We know that the Americans are very clever. If they can target a single person in a car from their planes, why did they have to blow up the whole building?”
The charity said it had recently recirculated GPS coordinates of the hospital to all parties fighting in the conflict, even though it has been operating for years and is one of few medical facilities in the city so should have been well known.
Human Rights Watch said it had serious concerns about whether US forces had taken sufficient precautions to avoid striking such a sensitive target. Hospitals are among areas protected from attack under international laws governing conflict.

Wednesday, September 30, 2015

Were Kansas voting machines programmed like VWs to record votes incorrectly only under certain conditions?/ IVN


by David Yee at IVN:
The VW case of tampering with the computing in their automobiles for emission tests once again highlights just how easy it is for a computer to “do” whatever it’s programmed to do — even if for nefarious reasons. With a simple switch inserted into the program, the output is factual when circumstances are one way and are tainted when it’s another way.
This is the fundamental claim that Dr. Beth Clarkson is making in the Kansas voting recount case. While Republicans were ahead, the votes were counted correctly, while Democrats (and independent Greg Orman) were ahead, it was almost like a switch was turned on to skew the results back to Republican.

So what’s the fundamental difference? Both the U.S. and German governments have pounced on VW’s software issues, launching full investigations, and assessing huge fines.
What has happened in any of the cases involving likely voter tampering of machines? Nothing.
Dr. Clarkson stated in her latest news letter that she now has both legal representation and a date for discovery — so the case is moving through the wheels of justice slowly.
But this is a sad reality. We jump on statistical anomalies that alert us to potential food contamination in our food supply, we test our water supplies daily for the same reason, and we test cars to make sure they are upholding legal emission standards. So why on earth are we not testing voting machines, something that has a complete and irreparable impact on our republican form of government?
The unwillingness of state officials, including Kansas Secretary of State Kris Kobach (the chief election officer), to do anything is only making this worse. And the problems will continue to get worse as America’s voting machines continue to age — with the oldest being about 15 years on average. These machines use outdated and unsupported operating systems, but they are still deemed “safe” for elections?
There has to be a balance between the quick delivery of election results on election night and the integrity of the vote itself. Because once human eyes are taken out of the equation, the fraud becomes greater and much harder to find.
For me, I’m alright with going to bed on election night not knowing the winner if it means that the system is more secure and our republic isn’t being ruled by “cyber-criminals” the next day.

Monday, September 21, 2015

China Probes Ex-Official Who Oversaw Clinical Trials for Bribery/ Bloomberg

Drugs and devices licensed in the US often rely on data generated overseas for FDA approval.  It should come as no surprise that FDA oversight of foreign clinical trials may be weak or nonexistent, and that drug/device approvals today seem more and more likely to be based on data whose reliability is far from assured...especially when the stakes are so high.  The cost of doing business for big pharma has included fines of billions of dollars, when they are occasionally found out.  

From the point of view of a physician, prescribing newly licensed drugs to patients is a nerve-wracking activity, as I have no assurance they are as safe and effective as claimed.  And they are assuredly more expensive than the old standards.  From Bloomberg

Chinese prosecutors announced a bribery investigation into a former national health official who for at least a decade oversaw clinical drug trials and implemented hospital policies. Wang Yu, the former director of the National Health and Family Planning Commission’s bureau of medical administration, has been arrested and is being investigated by prosecutors in the southwestern province of Sichuan, China’s Supreme People’s Procuratorate said on its website Tuesday. Bloomberg News reported earlier this month that Wang was suspected of violating Communist Party discipline, according to a person with direct knowledge of the matter, who asked not to be named because the probe wasn’t public.
Before retiring last year, Wang was responsible for supervising trials of drugs and medical devices, as well as drafting policies for medical institutions. The prosecutor’s statement Tuesday provided no details about bribery allegations against him.
The health industry is facing greater scrutiny in China, with the government in September fining British drugmaker GlaxoSmithKline Plc 3 billion yuan ($484 million) for paying bribes to win customers in the world’s most populous country. Authorities also last year started a preliminary probe into the business practices of foreign medical-equipment makers, people familiar with the matter said earlier this month.

Monday, September 7, 2015

The Real Afghanistan Surge is in Heroin Production and Tripled Opium Cultivation since the US military arrived/ UN and US Government documents


Recently I worked in another Maine city and was astonished at the number of patients I encountered who were using heroin. I had never seen anything like it, during a lifetime practicing medicine. In New Hampshire, it was said, deaths from heroin now exceed deaths from car accidents. Massachusetts (population under 7 million) had 1,000 deaths related to (all) opioids in 2014, "the highest ever recorded. According to CDC, in the two years between 2010 and 2012, heroin overdose rates in the Northeast tripled.  

The US now has 600,000 heroin users, triple the amount of five years earlier, according to the Drug Enforcement Agency.  Or it may instead have between 800,000 and 2.6 million, according to RAND report estimates published by the White House in 2014.

I've heard stories on NPR about insufficient state funding of heroin treatment facilities. I've heard about plans to make the antidote Narcan (naloxone) available to drug users, for overdoses. (Since I wrote this piece, a nasal spray version of Narcan has been approved for narcotic overdoses by FDA, and the drug may now be purchased without a prescription.) Another popular angle I've seen repeated over and over (and one currently pushed by the US Drug Enforcement Agency and the White House Office on National Drug Control Policy) claims legal prescriptions for narcotics increased, then became harder to get, so users switched to heroin, which was also cheaper.

Marijuana used to be claimed the "entry" drug to heroin, but now prescription narcotics have assumed that role. How times change. 

The narrative that has been presented to us implies that massively increased heroin use has nothing to do with increased supply. (This violates the laws of arithmetic and economics, not to mention common sense.) In Europe, West Asia and Russia, everyone knows their rising numbers of addicts reflects a huge increase in available heroin.  But the media obscure that fact, here.

If increased prescriptions for controlled substances was the primary cause of the heroin epidemic, then Americans would also be using more cocaine.  The massive increase in ADHD drug prescriptions (presumed "entry" drugs for cocaine) should have caused a cocaine explosion.

While prescriptions for narcotics (hydrocodone and oxycodone) increased 4.5-fold between 1991 and 2007 in the US, prescriptions for ADHD stimulants rose even more, by 7-fold, according to National Institute on Drug Abuse testimony to Congress in 2008


Total number of prescriptions dispensed by US retail pharmacies  - shows trends increasing from 1991 to 2007, see caption

But in fact, the DOJ-DEA 2014 National Drug Threat Assessment Summary notes that cocaine availability "remains stable at historically low levels throughout most domestic markets along the East Coast."  A RAND Report noted, "From 2006 to 2010, the amount of cocaine consumed in the United States declined by about 50 percent — an unprecedented change over five years."  There has been a parallel decline in methamphetamine use.

So prescription drug users are switching to heroin, but not switching to cocaine.  Might this be because we have no large military-CIA presence currently in cocaine-trafficking areas, as we did during the 1980s Contra war in Nicaragua, when cocaine use was at high levels? (Coca plants are only grown in South America's Andes.) According to a 2010 UN document"Based on seizure figures, it appears that cocaine markets grew most dramatically during the 1980s, when the amounts seized increased by more than 40% per year".  (See this 1987 Senate hearing and this for evidence of CIA and State Dept. connivance with cocaine trafficking by the Contras.)

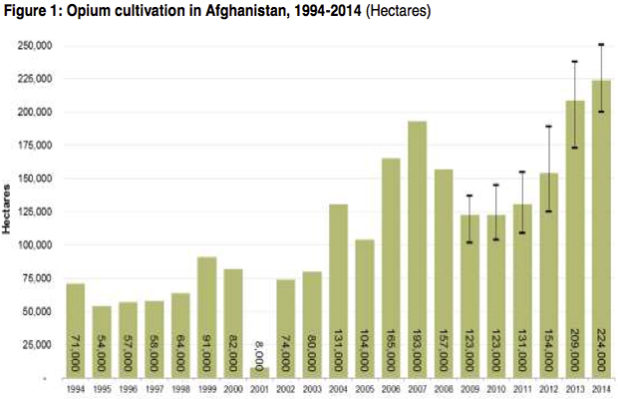
You can frame stories about the current heroin problem in many ways.  But the real heroin story isn't being discussed--which is that since the US military entered Afghanistan in 2001, its opium production doubled, per the UN Afghanistan Opium Survey 2014, page 34.  The area under opium cultivation in Afghanistan has tripled. And the resulting heroin appears to more easily make its way deep into our rural, as well as urban communities. CDC noted, "Between 2002 and 2013, the rate of heroin-related overdose deaths nearly quadrupled, and more than 8,200 people died in 2013." By 2014 there were 10,500 heroin overdose deaths, 6 times as many as in 2001.

The graph below is from the 2014 UN Opium Survey:


The world supply of opium increased 5-fold between 1980 and 2010according to the UN."Afghanistan account[s] for around 90% of global illicit opium production in recent years. By itself, Afghanistan provides 85% of the estimated global heroin and morphine supply, a near monopoly."(see pp 37-38).    
“The narcotics trade poisons the Afghan financial sector and undermines the Afghan state’s legitimacy by stoking corruption, sustaining criminal networks, and providing significant financial support to the Taliban and other insurgent groups,” John F. Sopko, the Special Inspector General for Afghanistan reconstruction, said in an October 2014 letter to the heads of the Departments of Defense, State and Justice, which have all played major roles in the failed drug intervention effort. “Despite spending over $7 billion to combat opium poppy cultivation and to develop the Afghan government’s counter-narcotics capacity, opium poppy cultivation levels in Afghanistan hit an all-time high in 2013."
Despite the (now) US $8.4 billion spent to defeat this trade, it just keeps growing.  The costs of US reconstruction efforts in Afghanistan total "$110 billion, after adjusting for inflation, [which] exceeds the value of the entire Marshall Plan effort to rebuild Western Europe after World War II" according to the Special Inspector General for Afghanistan Reconstruction, speaking in May 2015.

The Special Inspector General noted elsewhere that, "US reconstruction projects, particularly those devoted to “improved irrigation, roads, and agricultural assistance” were probably leading to the explosion in opium cultivation."

Only 1.2% of the acreage used for Afghan opium production (which is estimated at 224,000 hectares or 554,000 acres) was eradicated in 2014, according to the UN. Burma (now Myanmar) is the world's second largest producer of opium, according to the UN, currently growing only about 10% as much as Afghanistan. But Mexico has increased production and is #3.

According to the UN World Drug Report, in the 1990's Afghanistan supplied opium that was converted into half the world's heroin production.  According to University of Wisconsin Professor Alfred McCoy, the rapid 1980s rise in Afghani opium production came about through CIA efforts to create, arm and fund the mujahedeen using opium sales. (After defeating the Soviets in Afghanistan the mujahedeen morphed into Al Qaeda).  By 2010, Afghanistan supplied 90% of the world's total heroin.

But the DEAWhite House and other official US sources claim that US heroin derives almost entirely (96%) from Latin American-grown opium (based on seizures of shipments); the DEA in 2014 claimed that Latin America was the source for the vast majority of US heroin, with southwest Asia (i.e., Afghanistan) accounting for only 4% of US heroin in 2012. 

This is highly unlikely.  In 2008, the UN estimated that the US and Canada accounted for 13% of global heroin use.  Ninety-five percent of global heroin derives from Afghanistan, Burma, Thailand and Laos. Latin America (mainly Mexico, with a small amount from Colombia) does not produce enough to supply even half of US heroin, let alone 96%. In fact, the White House Office of National Drug Control Policy undercut its own claim when it noted Mexico had (only) 10,500 hectares under poppy cultivation in 2012 and Colombia 1,100 hectares in 2009, while Afghanistan had 154,000 hectares in 2012 and 224,000 hectares in 2014 per UN estimates.

This DEA claim, based on heroin interdiction, suggests something entirely different: that heroin shipments coming by air from Afghanistan are at lower risk of being seized than heroin coming from Latin America. Might some be entering via official government channels, when so much materiel and so many people (soldiers, aid workers, diplomats and contractors) fly directly between the US and Afghanistan? [At the same time, some Afghan-origin heroin does enter the US by way of Mexico.]

Putting aside the issue of the provenance of the US heroin supply for the moment, surely we can look at heroin as we would any other global commodity.

Congruent with the 1980s mujahedeen fight against the Soviets [here is the bland UN phrasing] : "...the Soviet invasion in 1979, [which] triggered the mass production of opiates in Afghanistan"and then -- in a repeat performance -- congruent with the US presence in Afghanistan since 2001, Afghanistan rapidly expanded opium production, and the global supply of heroin increased concomitantly. The price dropped as a result. New buyers entered the market. And the US now has, at least, several hundred thousand new addicts.  Russia and the rest of Europe (with overland access to Afghanistan) have even more. The resulting social problems are hugely tragic and hugely costly for millions of families, and for our societies as a whole. 

If we start being honest about why there is a major heroin epidemic, maybe we can get serious about solving the problem with meaningful eradication and interdiction. Aerial spraying of crops with herbicides or similar methods has been prohibited in Afghanistan, but it works. In 2014, Britain's former Ambassador to Afghanistan (2010-2012) called for legalization and regulation of illicit drugs as one means of attacking the problem.  

Looking beyond the Mexican border for heroin, and inspecting all flights from southwest Asia, including military and CIA flights, could have a large impact on supply as well.

Serious measures are needed.  Total world production of opiates always gets consumed: historically, the market for opiates has been extremely elastic.  Land under poppy cultivation (in Afghanistan, Southeast Asia's Golden Triangle and Mexico) continues to increase. Without meaningful efforts to reduce opium production and entry of narcotics into the US, the epidemic of heroin addiction could become a considerably bigger problem than it is today.

UPDATE:  From the Sept 7 Wall Street Journal, we learn that a US "friendly fire" airstrike in southern Afghanistan on Sept 6 "hit a 30 member elite counternarcotics police unit as they were on a mission...


At least 11 died in "one of the deadliest friendly fire incidents in the country in recent years." Here is the Reuters story. The US denied the strike in Helmand province, but admitted to airstrikes in the adjacent province of Kandahar. According to the Guardian, "The US is the only member of the NATO coalition known to have carried out bombing raids in Afghanistan this year." The AP/WaPo on 9/8/15 reported that, "Brigadier General Shoffner [Deputy Chief of Staff for Communications in Afghanistan] said 'based on information we received [on 9/8], we feel it is prudent to investigate the airstrike our forces conducted in Kandahar.'"


The airstrike killed approximately as many people as died in counternarcotics efforts in all Afghanistan throughout 2014.


UPDATE:  Helmand is the major opium-producing province in Afghanistan; military efforts in Helmand are managed primarily by the UK.  In 2010, the magazine The Week accused UK soldiers of importing heroin back to Europe and Canada in military planes.

UPDATE:  I have marshalled considerably more evidence about the false narratives that been spread regarding the current heroin epidemic.  Their purpose is to misdirect us away from the true cause (massively increased heroin entering the US) and solutions (interdicting or destroying the Afghan opium crop).  

Since I wrote this piece, the US's top General in Afghanistan, John Campbell, told Congress we need a five year plan for US and NATO involvement in Afghanistan. What precisely are we doing there?  What does CIA do there? Why has the US military been prevented from stopping opium production in territories it controls?  Does an even worse Afghan heroin epidemic in Russia affect US strategic thinking?  What did Hillary Clinton know and do about rising Afghan heroin production during her time as Secretary of State?  Why aren't these questions being asked of our Presidential candidates?

Let me credit Professor Alfred McCoy's work, which provided me historical background: he is probably the world's foremost scholar on the subject of the global production and trade in illicit drugs.
 

Saturday, September 5, 2015

"One Less" country--Japan--swallows Merck's lies about its HPV vaccine; Japan establishes guidelines and special clinics to treat HPV vaccine-injured girls/ Medscape

Vaccine injuries are real.  They can be serious and often fail to respond to treatment. The most serious injuries are usually to the brain. Vaccine injuries may cause death. The US' federal vaccine injury compensation program has paid out $3.18 billion dollars in compensation for vaccine injuries since the program was established in 1988. 
Yet with the stoking of fears over measles and the claimed desperate need for vaccine mandates in 2015, these truths about vaccine injuries have been overlooked, or deliberately ignored by the media.
It is hard to believe, but there is lack of proof that HPV vaccines actually prevent cervical cancer.  That is why I have published an excerpt from FDA's initial Gardasil approval letter below.  Gardasil HPV vaccine was licensed under "fast-track" authority by FDA in 2006 with limited data and its manufacturer, Merck, was required by FDA to collect data through 2017 to determine whether Gardasil really does prevent cancer:
  1. You have committed to collaborate with the cancer registries in four countries in the Nordic Region ( Sweden, Norway, Iceland, and Denmark) to assess long-term outcomes following administration of GARDASI®. In this study, approximately 5,500 subjects enrolled in Protocol 015 (one half from the placebo group that will have been vaccinated shortly after approval) will be followed for a total of 14 years. Two major goals of this study are: 1) to assess the long-term effectiveness of GARDASIL® by evaluating biopsy specimens for presence of HPV 6/11/16/18-related incident breakthrough cases of CIN 2/3, AIS and cervical cancer, VIN 2/3 and vulvar cancer, and VaIN 2/3 and vaginal cancer; and 2) to assess whether administration of GARDASIL® will result in replacement of these diseases due to vaccine HPV types with diseases due to non-vaccine HPV types. This study is designed to accomplish these goals as discussed in the June 6, 2006, submission to your BLA. The final protocol for this study will be submitted by December 8, 2006. Patient accrual for this study was previously completed in the context of Protocol 015. This study will be completed by December 31, 2017, (14 years from initiation of the last patient enrolled in Protocol 015 in the four Nordic countries). The final study report will be submitted by December 31, 2018...--from FDA to Merck
Furthermore, the Gardasil label explicitly notes that recipients must still have regular PAP smears, precisely because it is not clear Gardasil prevents the development of cancer, while PAP smears enable early detection and treatment before a cervical lesion evolves into cancer:
"...Limitations of GARDASIL Use and Effectiveness:• GARDASIL does not eliminate the necessity for women to continue to undergo recommended cervical cancer screening..."
So the vaccine may work.  Or it may not.  But that has not stopped some states and countries from recommending or requiring this vaccine (intended for a sexually transmitted disease) for all children in junior high school.  Rhode Island just mandated HPV vaccine for all 7th grade students in July 2015. 

How safe are HPV vaccines? We lack reliable data, but there are many reports of serious injuries. 

Now Japan (after 358 vaccine injuries judged serious and 2,000 adverse event reports) has not only rescinded its recommendation that girls receive this vaccine, but has also established guidelines and special clinics for evaluating and treating illnesses caused by the Gardasil and Cervarix HPV vaccines.
From Medscape:
"Japan has put in place a scheme to manage symptoms, especially generalized chronic pain, that have arisen after human papillomavirus (HPV) vaccination given to adolescents to protect against cervical cancer.
Although there have been assurances on the safety of HPV vaccination from many official medical bodies since the vaccines were first introduced — Gardasil (Merck & Co.) in 2006 and Cervarix (GlaxoSmithKline) in 2009 — there have also been persistent reports of rare cases of adverse events. These include case reports in the medical literature of complex regional pain syndrome and postural orthostatic tachycardia syndrome, as previously reported by Medscape Medical News.
In July 2015, the European Medicines Agency announced that it was conducting a safety review of HPV vaccines, which was requested by Denmark, where reports of adverse events after HPV vaccination have been widely reported in the media.
Japan withdrew its recommendation for HPV vaccine in 2013, and has not reversed that decision because of concerns from the public about adverse events, which included long-term pain and numbness, as previously reported by Medscape Medical News.
Since then, various symptoms, especially generalized chronic pain after injection, have been reported.
Last month, guidelines for the evaluation and management of symptoms that begin after HPV vaccine injection were issued to healthcare professionals. The guidelines were edited and approved by the Japan Medical Association (JMA) and the Japanese Association of Medical Sciences (JAMS).
In addition, the Japanese Ministry of Health, Labor, and Welfare has issued a list of medical institutions where people can visit when they have symptoms after HPV injection; there is at least one in each prefecture. Healthcare workers at those selected institutions are educated by the JMA. However, this does not mean other institutions cannot accept those people with symptoms. The ministry has also issued information regarding HPV vaccine-related health problems and questions, with a telephone helpline..."